
Stabilizing the Neck and Protecting the Spinal Cord
When the neck is unstable, out of alignment, or the spinal cord is compressed at several levels, a posterior cervical fusion can often correct the problem by stabilizing the neck and protecting the spinal cord.
What Is a Posterior Cervical Fusion?
A posterior cervical fusion is a surgery done through the back of the neck to join two or more vertebrae so they heal into one solid bone. Small screws are placed into the vertebrae and connected with rods, and bone graft is added so the bones fuse together over the following months.
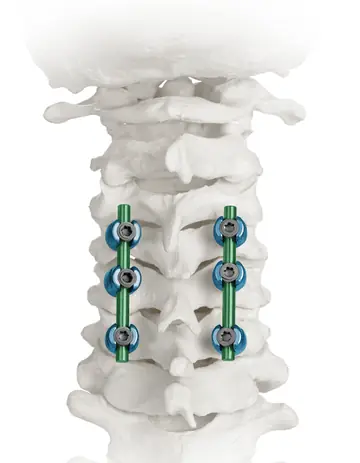
A posterior cervical fusion is often combined with a cervical laminectomy, which removes the bony roof of the spinal canal to take pressure off the spinal cord. The fusion keeps the neck stable and helps prevent it from gradually bending forward after the laminectomy. It can also be combined with surgery from the front of the neck, such as an ACDF, for complex problems.
Who Needs a Posterior Cervical Fusion?
- Cervical myelopathy from stenosis at several levels, treated with a laminectomy and fusion
- OPLL or severe cervical spondylosis
- Instability of the neck from arthritis, injury or a previous surgery
- Neck deformity, such as the neck bending forward (cervical kyphosis)
- Fractures, tumors or infection that have weakened the neck
- A previous front-of-the-neck fusion that didn’t heal
Call 911 or go to the nearest emergency room if you have sudden weakness in your arms or legs, sudden trouble walking, or new trouble controlling your bladder or bowels.
Treatments to Try First
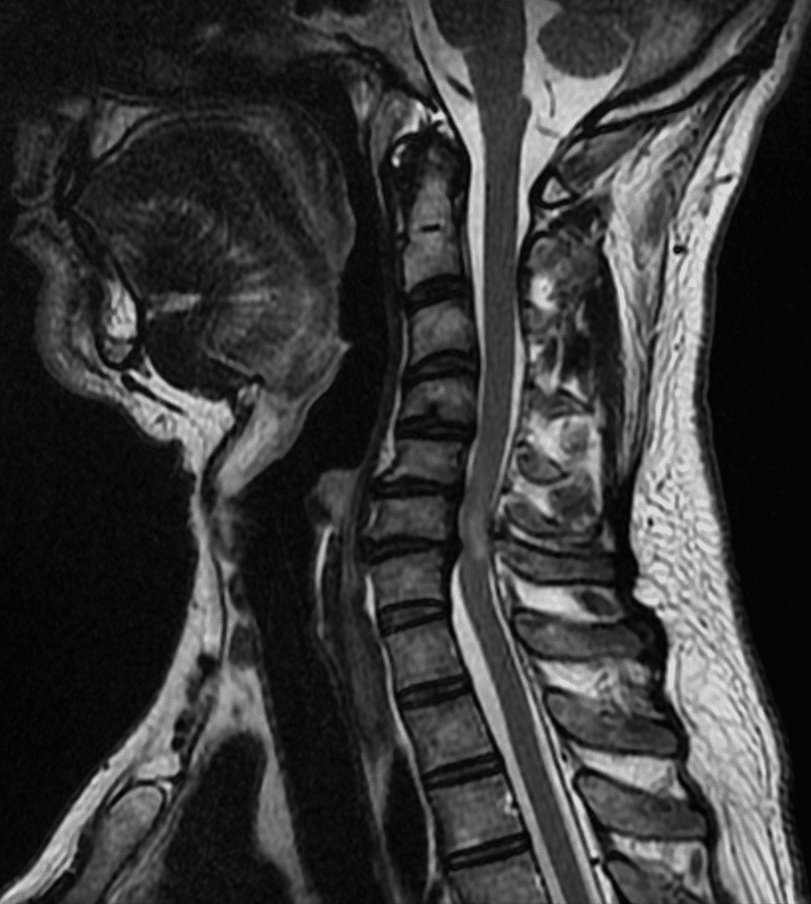
For neck pain or a pinched nerve without instability or spinal cord compression, physical therapy, medications and injections are usually tried first. When the spinal cord is compressed or the neck is unstable, these treatments can’t fix the underlying problem, and surgery can often correct the problem and prevent further damage.
How a Posterior Cervical Fusion Is Done
- Anesthesia and monitoring: You’ll be fully asleep. Nerve monitoring protects the spinal cord and nerves throughout surgery.
- Positioning: Your head is held securely in a padded frame, and you’re positioned face down.
- Incision: An incision is made down the middle of the back of the neck over the levels to be fused.
- Decompression, if needed: The lamina and thickened ligaments are removed to free the spinal cord and nerves.
- Placing screws and rods: Using X-ray or navigation, small screws are placed into the vertebrae and connected with rods.
- Bone graft: Bone graft is placed along the back of the spine so the vertebrae fuse together.
- Closing: The muscles and skin are closed in layers.
Watch an animation of how a posterior cervical fusion is done:
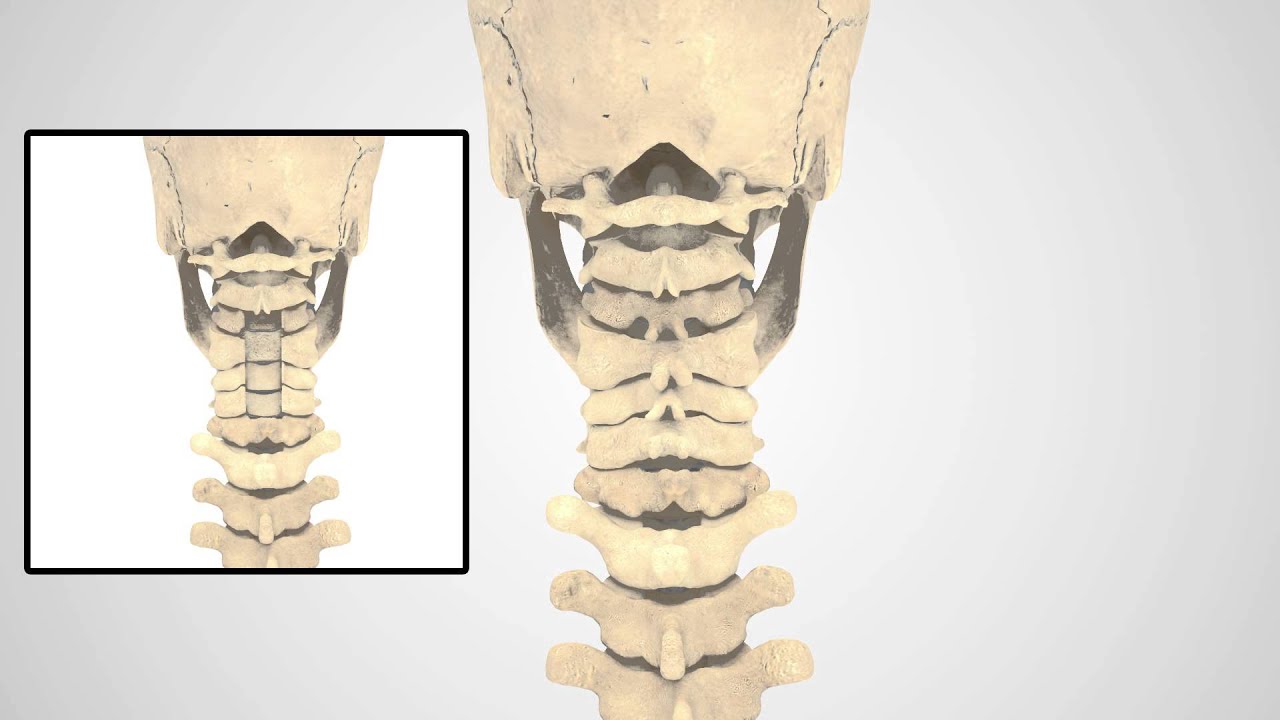
Video: PCF Patient Animation, courtesy of NuVasive (YouTube)
Benefits and Risks
Benefits
- A stable neck and protection of the spinal cord
- Can treat many levels in one surgery
- Helps prevent the neck from bending forward after a laminectomy
- Improves arm pain, numbness, hand function or balance for many patients
Risks
- Infection or wound healing problems
- Bleeding or a spinal fluid leak
- Temporary weakness lifting the arm at the shoulder (C5 palsy), which usually improves
- Neck pain and stiffness, and reduced motion at the fused levels
- The bones not fusing, or screw loosening
- Spinal cord or nerve injury, which is rare
- Risks related to anesthesia
Why Choose Dr. Betsy Grunch for Your Posterior Cervical Fusion
- Duke-trained: Dr. Grunch completed her neurosurgical residency and a spine research fellowship at Duke University School of Medicine, one of the top neurosurgery programs in the country, where she received the Spine Young Investigator Award.
- Fusion only when you need it: She also performs lumbar and cervical disc replacement and decompression without fusion, so a fusion is recommended only when it’s truly the best option for you.
- Experience you can count on: She has been in practice since 2013 and performs 400 to 600 surgeries a year, more than 5,000 procedures over her career.
- Every option for your neck: She performs posterior cervical fusion, laminoplasty, ACDF and cervical disc replacement, so your recommendation is based on what’s best for you.
- Second opinions and revisions: She regularly sees patients who had spine surgery elsewhere and want a second opinion or need a revision.
- A teacher at heart: As “Ladyspinedoc,” she is known for explaining spine conditions clearly. You’ll leave your visit understanding your imaging and every option in front of you.
What to Expect
Before surgery
You’ll meet with Dr. Grunch or one of her physician assistants to review your imaging, your exam and your goals, and to decide together whether a posterior cervical fusion is right for you. Our team will coordinate any pre-operative testing, review your medications (including blood thinners you may need to pause) and walk you through the day of surgery so nothing is a surprise. Smoking and nicotine slow bone healing and can cause a fusion to fail, so stopping before surgery is strongly recommended. Our office can help.
Procedure day
Surgery usually takes two to four hours, depending on the number of levels. Most patients stay in the hospital for one to three nights.
Recovery timeline
- First two weeks: Neck soreness and muscle spasms are common. Walk every day. You may wear a collar for comfort or support as directed.
- Four to six weeks: Your follow-up visit, with X-rays to check healing. Many people return to desk work around this time.
- Six to twelve weeks: Physical therapy helps rebuild neck and shoulder strength.
- Six to twelve months: The bones continue to fuse. Balance and hand function may keep improving.
Every patient heals differently. Your exact timeline will depend on your symptoms, the number of levels fused, your job and your overall health.
Caring for yourself at home
- Walking: Walk 30 to 60 minutes a day, broken into short sessions.
- Restrictions for about six weeks: No lifting more than 10 pounds and no working above shoulder level.
- Medications: Avoid anti-inflammatory medications such as ibuprofen and naproxen, which can interfere with fusion. Blood thinners are held until Dr. Grunch’s team tells you to restart them.
- Driving: You may drive once you’re off narcotic pain medication and can turn your head comfortably.
If you go home in a cervical collar, watch how to wear it correctly:
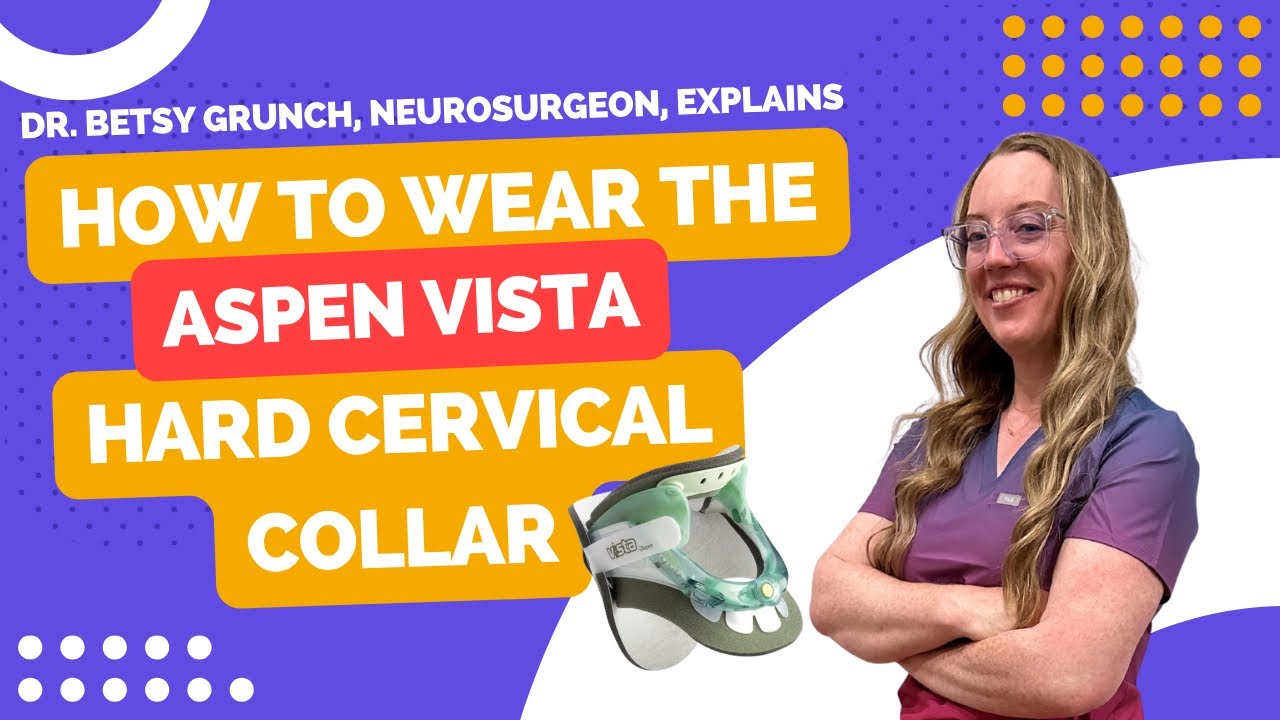
Video: How to Correctly Wear the Aspen Vista Cervical Collar, from Dr. Grunch on her Ladyspinedoc channel (YouTube)
Call the office at 470-293-9800 if you have a fever over 101°F, redness, warmth or drainage from the incision, calf pain or swelling, or new or worsening weakness. Call 911 for chest pain or shortness of breath.
Frequently Asked Questions
Will I be able to turn my head?
Yes, though motion is reduced at the fused levels. Most people adapt well for daily activities and driving, especially when the top of the neck isn’t included in the fusion.
Why fuse after a laminectomy?
Removing the laminae at several levels can let the neck slowly bend forward over time. A fusion keeps it stable and in good alignment.
Will I wear a neck collar?
Some patients wear a collar for a short time for comfort or support. Dr. Grunch will let you know if you need one.
Could I have a laminoplasty instead?
Possibly. A laminoplasty widens the canal without a fusion and preserves more motion, but it isn’t right for necks that are unstable or have lost their normal curve.
Why can’t I take ibuprofen after surgery?
Anti-inflammatory medications can interfere with bone healing. Dr. Grunch’s team will tell you when it’s safe to restart them.
You’ll find instructions for other procedures on our Patient Resources page.
Take the First Step Toward Relief
Neck instability and spinal cord compression shouldn’t be ignored. Whether you need a treatment plan, a second opinion or a clear explanation of your imaging, Dr. Grunch and the Southern Neurosurgery team are here to help.
Call 470-293-9800 to schedule an appointment or contact us online.
Have a question first? Ask our virtual assistant anything, 24/7.
We see patients across metro Atlanta and North Georgia at our offices in Gainesville, Sandy Springs and South Atlanta (Riverdale). Find the office nearest you.
Related pages: Cervical myelopathy · Cervical laminectomy · Laminoplasty · ACDF · OPLL
This page is for educational purposes only and is not medical advice. It does not replace individualized care from a licensed physician. Please talk with your own doctor about your symptoms. If you have bladder or bowel changes, groin numbness or rapidly worsening weakness, call 911 or go to the nearest emergency room.