
Spinal Fusion Through Smaller Incisions
A spinal fusion doesn’t have to mean a long incision and weeks in recovery. Minimally invasive fusion can often correct the problem through small incisions, with less pain and a faster return to your life.
What Is a Minimally Invasive Fusion?
A minimally invasive fusion stabilizes one or more levels of the spine using small incisions, special retractors and live image guidance instead of a large open incision. The goal is the same as a traditional lumbar fusion: remove the damaged disc, take pressure off the nerves, and let the vertebrae heal into one solid bone. The difference is how the surgeon gets there.
In open surgery, the back muscles are stripped away from the spine to see it. In minimally invasive surgery, the muscles are gently separated and held aside with a small tube-shaped retractor, and screws are placed through the skin using X-ray or navigation. Less muscle damage usually means less pain, less blood loss, a shorter hospital stay and a quicker recovery.
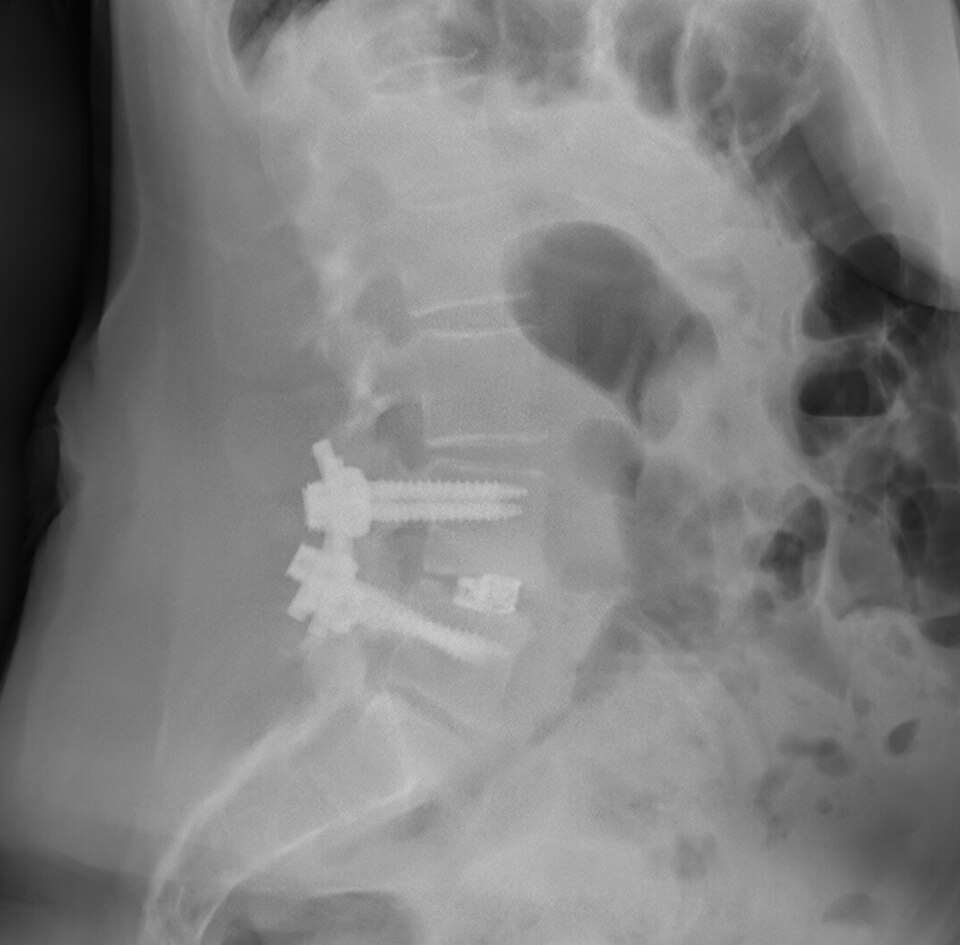
Minimally invasive spine surgery is one of Dr. Grunch’s signature areas, including transforaminal approaches through Kambin’s triangle, a small natural window to the disc that avoids the nerves.
Types of Minimally Invasive Fusion
- MIS TLIF (minimally invasive transforaminal lumbar interbody fusion): the most common type. Through a small incision on one side of the back, the disc is removed and a spacer with bone graft is placed, followed by screws and rods through small incisions.
- LLIF (lateral lumbar interbody fusion): the disc is reached through a small incision on the side of the body.
- OptiLIF: an ultra-minimally invasive fusion that uses an expandable mesh bag filled with bone graft, placed through a very small working portal.
- Percutaneous screw fixation: screws and rods placed through the skin, used alone or with any of the above.
Who Is a Candidate?
- Spondylolisthesis or spinal instability at one or two levels
- Degenerative disc disease or a collapsed disc causing back and leg pain
- Foraminal stenosis from a collapsed disc
- A recurrent disc herniation at the same level
- Adjacent segment disease above or below a previous fusion
Not everyone is a candidate. Severe deformity, multiple levels or complex revisions sometimes need an open approach. Dr. Grunch will explain which option is safest and most effective for you.
Treatments to Try First
- Physical therapy: core strengthening and a structured exercise program
- Medications: anti-inflammatory medications, muscle relaxers or nerve pain medications
- Injections: epidural steroid injections or facet injections
When these no longer keep you active, surgery can often correct the problem.
How a Minimally Invasive Fusion Is Done
- Anesthesia and monitoring: You’ll be fully asleep, and nerve monitoring protects the nerves.
- Small incisions: Using X-ray or navigation, small incisions are made over the level to be fused.
- Muscle-sparing access: The muscles are gently separated and held with a tube-shaped retractor rather than cut.
- Decompression and disc removal: Under magnification, the nerves are freed and the disc is removed.
- Placing the spacer: A spacer filled with bone graft is placed to restore disc height and alignment.
- Percutaneous screws: Screws and rods are placed through small incisions to hold the level steady.
- Closing: The small incisions are closed with dissolvable stitches and skin glue.
Benefits and Risks
Benefits
- Smaller incisions and less muscle damage
- Less pain and less blood loss
- A shorter hospital stay, often one night
- A faster return to walking, work and daily activities
- Fusion rates similar to open surgery for well-selected patients
Risks
- Infection or bleeding
- The bones not fusing, which is more common in people who smoke
- Screw or spacer loosening, which can require another surgery
- Nerve irritation or injury, or a spinal fluid leak, which are uncommon
- Wear at neighboring levels over time
- Risks related to anesthesia, including blood clots
Why Choose Dr. Betsy Grunch for Your Minimally Invasive Fusion
- Duke-trained: Dr. Grunch completed her neurosurgical residency and a spine research fellowship at Duke University School of Medicine, one of the top neurosurgery programs in the country, where she received the Spine Young Investigator Award.
- Minimally invasive by design: Minimally invasive spine surgery, including transforaminal approaches through Kambin’s triangle, is one of her signature areas, so you can get back on your feet sooner.
- Fusion only when you need it: She also performs lumbar and cervical disc replacement and decompression without fusion, so a fusion is recommended only when it’s truly the best option for you.
- Experience you can count on: She has been in practice since 2013 and performs 400 to 600 surgeries a year, more than 5,000 procedures over her career.
- Second opinions and revisions: She regularly sees patients who had spine surgery elsewhere and want a second opinion or need a revision.
- A teacher at heart: As “Ladyspinedoc,” she is known for explaining spine conditions clearly. You’ll leave your visit understanding your imaging and every option in front of you.
What to Expect
Before surgery
You’ll meet with Dr. Grunch or one of her physician assistants to review your imaging, your exam and your goals, and to decide together whether a minimally invasive fusion is right for you. Our team will coordinate any pre-operative testing, review your medications (including blood thinners you may need to pause) and walk you through the day of surgery so nothing is a surprise. Smoking and nicotine slow bone healing and can cause a fusion to fail, so stopping before surgery is strongly recommended. Our office can help.
Procedure day
Surgery usually takes two to three hours. Most patients stay one night in the hospital and are up and walking the day of surgery or the next morning.
Recovery timeline
- First two weeks: Leg pain often improves quickly. Walk several times a day and wear your brace when you’re up.
- Two to six weeks: Many people with desk jobs return to work. Your follow-up visit is at four to six weeks, with X-rays to check healing.
- Six to twelve weeks: Restrictions are gradually lifted, and physical therapy may begin.
- Six to twelve months: The bones continue to fuse, and most patients are back to normal activities.
Every patient heals differently. Your exact timeline will depend on your symptoms, the number of levels fused, your job and your overall health.
Caring for yourself at home
- Back brace: Wear your brace whenever you’re out of bed and moving around.
- Walking: Walk 30 to 60 minutes a day, broken into 10- to 15-minute sessions, and try not to sit for more than 30 minutes at a time.
- Restrictions for about six weeks: No bending at the waist, no twisting and no lifting more than 10 pounds. That includes vacuuming, laundry, golf, yard work and lifting young children or grandchildren. Let others help you at home.
- Your incision: If your incision is closed with skin glue, you may shower the day after surgery; if it has stitches or staples, wait three days. Don’t scrub, don’t use ointments or creams, and don’t soak in a bath, hot tub or pool for six weeks.
- Medications: Avoid anti-inflammatory medications such as ibuprofen, naproxen, meloxicam, celecoxib and diclofenac, which can interfere with fusion. Blood thinners are held for 5 to 7 days after surgery until Dr. Grunch’s team tells you to restart them. Take pain medication with food, avoid alcohol while taking it, and use a daily stool softener.
- Bone growth stimulator: If one is prescribed, the manufacturer will contact you after surgery.
- Driving: You may drive once you are no longer taking narcotic pain medication, and you may ride as a passenger before then.
- Follow-up: Your follow-up visit is about four to six weeks after surgery. Any outside stitches or staples are removed at 10 to 14 days.
Learn how a bone growth stimulator can support your fusion:

Video: Spinal Fusion Patients: Are You Using a Bone Growth Stimulator?, from Dr. Grunch on her Ladyspinedoc channel (YouTube)
Call the office at 470-293-9800 if you have a fever over 101°F, redness, warmth or significant drainage from the incision, calf pain or swelling, constipation that medication doesn’t relieve, new trouble controlling your bladder or bowels, or worsening pain down your leg. Call 911 for chest pain or shortness of breath.
Download your patient packet
Print the packet for your surgery or save it to your phone so you have it before and after surgery. Each packet explains your surgery, includes your post-operative instructions and shows how to reach our 24/7 Virtual Assistant:
- Patient packet: Transforaminal Lumbar Interbody Fusion (TLIF) (PDF)
- Patient packet: Lateral Lumbar Interbody Fusion (LLIF) (PDF)
See all patient packets to find instructions for other surgeries and our Surgery Day Guides.
Frequently Asked Questions
Is a minimally invasive fusion as strong as an open fusion?
For well-selected patients, studies show similar fusion rates and outcomes, with less pain and a faster recovery.
How big are the incisions?
Usually a few small incisions about an inch long, instead of one long incision down the middle of the back.
Will I need a brace?
Most patients wear a back brace when out of bed during the first several weeks.
Why can’t I take ibuprofen after surgery?
Anti-inflammatory medications can interfere with bone healing. Dr. Grunch’s team will tell you when it’s safe to restart them.
When can I drive and go back to work?
You may drive once you’re off narcotic pain medication. Many people with desk jobs return in two to six weeks, while physically demanding jobs take longer.
Take the First Step Toward Relief
If you’ve been told you need a fusion, ask whether it can be done through smaller incisions. Whether you need a treatment plan, a second opinion or a clear explanation of your imaging, Dr. Grunch and the Southern Neurosurgery team are here to help.
Call 470-293-9800 to schedule an appointment or contact us online.
Have a question first? Ask our virtual assistant anything, 24/7.
We see patients across metro Atlanta and North Georgia at our offices in Gainesville, Sandy Springs and South Atlanta (Riverdale). Find the office nearest you.
Related pages: TLIF · LLIF · Lumbar fusion · OptiLIF · Spondylolisthesis · Spinal instability · Degenerative disc disease
This page is for educational purposes only and is not medical advice. It does not replace individualized care from a licensed physician. Please talk with your own doctor about your symptoms. If you have bladder or bowel changes, groin numbness or rapidly worsening weakness, call 911 or go to the nearest emergency room.