
Lumbar Fusion From the Front of the Spine
When a worn-out or slipping disc low in the back is causing pain, an anterior lumbar interbody fusion (ALIF) can often correct the problem by rebuilding the disc space from the front and letting the spine heal into one solid, stable segment.
What Is an ALIF?
An anterior lumbar interbody fusion, or ALIF, is a type of lumbar fusion done through a small incision in the lower abdomen. “Anterior” means front. Instead of going through the back muscles, the surgeon gently moves the abdominal contents and the large blood vessels aside to reach the front of the spine.
The damaged disc is removed and replaced with a large spacer (cage) filled with bone graft. Because the front of the spine is wide open, the spacer can be bigger than with other approaches, which helps restore disc height, open the nerve passages and rebuild the natural inward curve of the lower back. Over the following months, the bone graft grows through the spacer and fuses the two vertebrae together.
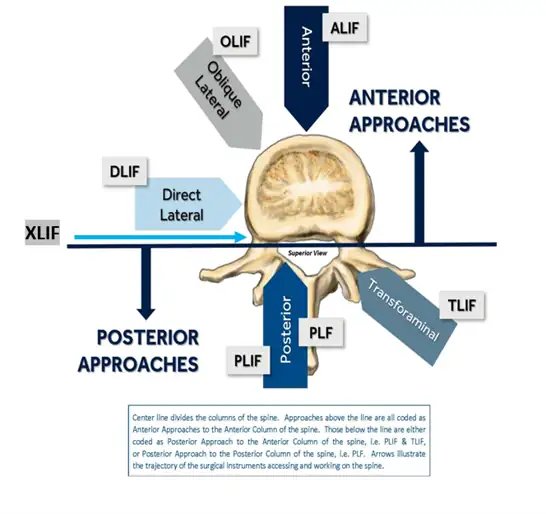
ALIF is most often used at the lowest levels of the spine, L4-L5 and L5-S1. Depending on your needs, it can be done on its own with a plate or screws in the front, or combined with screws placed through small incisions in the back for extra stability.
Who Needs an ALIF?
- Degenerative disc disease or a collapsed disc at L4-L5 or L5-S1 causing back and leg pain
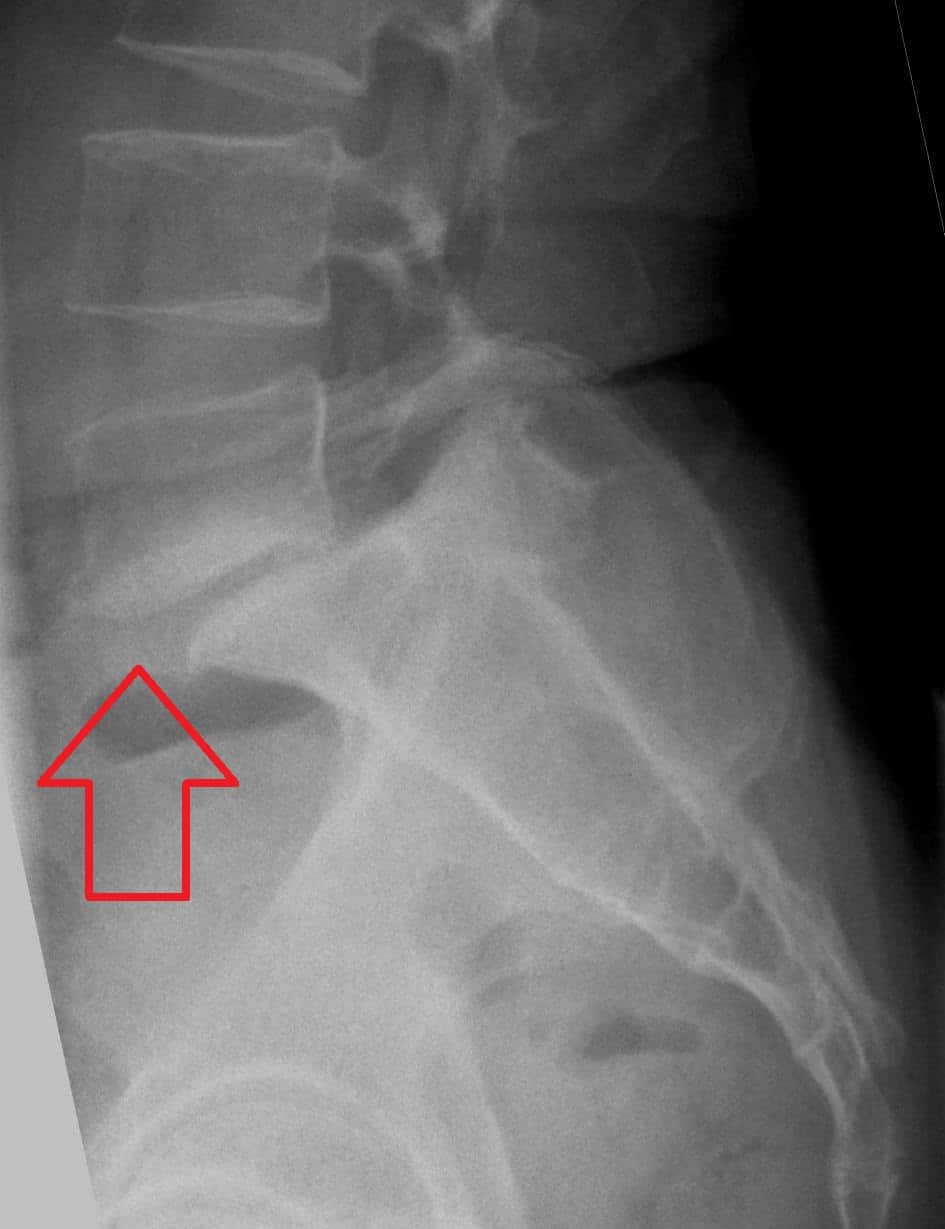
- Spondylolisthesis, where one vertebra slips forward over another
- Foraminal stenosis from a collapsed disc pinching the exiting nerve
- Discogenic back pain that hasn’t improved with nonsurgical care, when disc replacement isn’t an option
- Loss of the natural lower back curve (flatback) or adjacent segment disease below a previous fusion
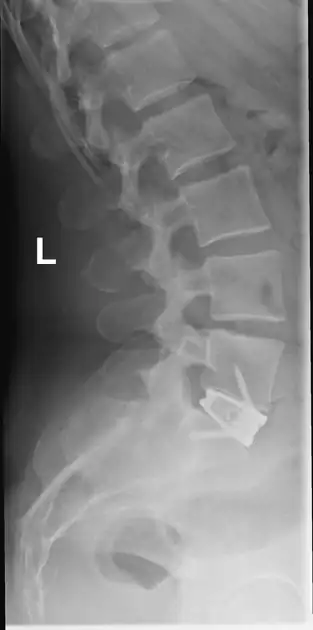
- A failed fusion from the back that needs to be repaired from the front (revision fusion)
ALIF isn’t right for everyone. Previous major abdominal surgery, certain blood vessel anatomy or significant scarring can make the front approach less safe. Dr. Grunch reviews your imaging carefully and may recommend a lateral (LLIF) or transforaminal (TLIF) approach instead.
Treatments to Try First
- Physical therapy: core strengthening and a structured exercise program
- Medications: anti-inflammatory medications, muscle relaxers or nerve pain medications
- Injections: epidural steroid injections, facet injections or radiofrequency ablation
- Activity changes and weight management to reduce stress on the spine
When these no longer keep you active, or nerves are being compressed by slipping or instability, surgery can often correct the problem.
How an ALIF Is Done
- Anesthesia and positioning: You’ll be fully asleep and lying on your back.
- Reaching the spine: A small incision is made in the lower abdomen. An access surgeon (a vascular or general surgeon) often works alongside Dr. Grunch to carefully move the abdominal contents and the major blood vessels aside, without cutting through the abdominal muscles.
- Removing the disc: The damaged disc is removed and the bone surfaces are prepared so they can fuse.
- Placing the spacer: A large spacer filled with bone graft is placed to restore disc height and alignment.
- Stabilizing: The spacer may be secured with a plate or screws in the front. Some patients also need screws placed through small incisions in the back.
- Closing: Everything is returned to its normal position and the incision is closed with dissolvable stitches and skin glue.
Watch an animation of how an ALIF is done:
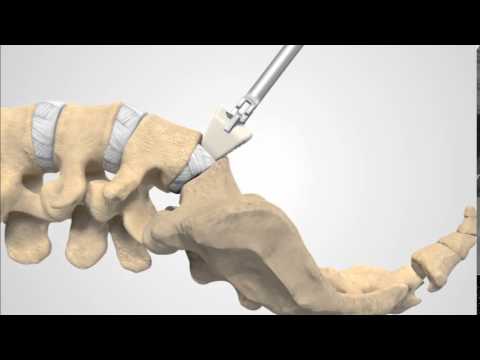
Video: ALIF Patient Animation, courtesy of NuVasive (YouTube)
This video walks through an ALIF at L5-S1:
Video: ALIF (Anterior Lumbar Interbody Fusion), courtesy of Spine-health
Benefits and Risks
Benefits
- The back muscles are left untouched, which can mean less back pain after surgery
- A large spacer gives excellent restoration of disc height and lower back curve
- Indirect relief for pinched nerves as the disc space and nerve openings are restored
- A large surface for the bone to heal across, which supports a strong fusion
Risks
- Infection or bleeding
- Injury to the large blood vessels in front of the spine, which is uncommon but serious
- A temporary slowdown of the bowels (ileus), which is why you start on a liquid diet
- A hernia at the incision
- In men, a rare risk of retrograde ejaculation, which can affect fertility
- The bones not fusing (nonunion), which is more common in people who smoke
- Extra wear at the levels above or below the fusion over time (adjacent segment disease)
- Risks related to anesthesia, including blood clots
Why Choose Dr. Betsy Grunch for Your ALIF
- Duke-trained: Dr. Grunch completed her neurosurgical residency and a spine research fellowship at Duke University School of Medicine, one of the top neurosurgery programs in the country, where she received the Spine Young Investigator Award.
- Anterior surgery done as a team: She partners with experienced access surgeons for the front approach, so each part of your surgery is done by a specialist.
- Every approach: She performs TLIF, PLIF, ALIF and LLIF and chooses the approach that best fits your anatomy rather than using one technique for everyone.
- Fusion only when you need it: She also performs lumbar disc replacement and decompression without fusion, so a fusion is recommended only when it’s truly the best option for you.
- Experience you can count on: She has been in practice since 2013 and performs 400 to 600 surgeries a year, more than 5,000 procedures over her career.
- Second opinions and revisions: She regularly sees patients who had spine surgery elsewhere and want a second opinion or need a revision.
- A teacher at heart: As “Ladyspinedoc,” she is known for explaining spine conditions clearly. You’ll leave your visit understanding your imaging and every option in front of you.
What to Expect
Before surgery
You’ll meet with Dr. Grunch or one of her physician assistants to review your imaging, your exam and your goals, and to decide together whether an ALIF is right for you. Our team will coordinate any pre-operative testing, review your medications (including blood thinners you may need to pause) and walk you through the day of surgery so nothing is a surprise. Smoking and nicotine slow bone healing and can cause a fusion to fail, so stopping before surgery is strongly recommended. Our office can help.
Procedure day
Surgery usually takes two to four hours, longer if screws are also placed from the back. Most patients stay in the hospital for one to three nights. You’ll start on a liquid diet while your bowels wake up, then move to regular food once they’re working. You’ll be up and walking by the day after surgery, and physical therapy will help you get moving safely before you go home. A sore throat from the breathing tube is common and usually improves within a week.
Recovery timeline
- First two weeks: Leg pain often improves quickly. Soreness in the belly and back is normal. Walk several times a day and wear your brace when you’re up.
- Four to six weeks: Your follow-up visit, with X-rays to check healing. Many people with desk jobs return to work in three to six weeks.
- Six to twelve weeks: Restrictions are gradually lifted, and physical therapy may begin to strengthen your core.
- Six to twelve months: The bones continue to fuse. Most patients are back to their normal activities.
Every patient heals differently. Your exact timeline will depend on your symptoms, the number of levels fused, your job and your overall health.
Watch Dr. Grunch’s post-op care instructions:

Video: Post-op Care for Anterior Lumbar Interbody Fusion (ALIF), from Dr. Grunch on her Ladyspinedoc channel (YouTube)
Caring for yourself at home
- Back brace: Wear your brace whenever you’re out of bed and moving around.
- Walking: Walk 30 to 60 minutes a day, broken into 10- to 15-minute sessions, and try not to sit for more than 30 minutes at a time.
- Restrictions for about six weeks: No bending at the waist, no twisting and no lifting more than 10 pounds. That includes vacuuming, laundry, golf, yard work and lifting young children or grandchildren. Let others help you at home.
- Your incision: Your incision is on the front of your belly. If it is closed with skin glue, you may shower the day after surgery; if it has stitches or staples, wait three days. Gently wash, pat dry and leave it open to air. A small amount of brownish-red ooze for a few days is normal. Don’t scrub, don’t use ointments or creams, and don’t soak in a bath, hot tub or pool for six weeks.
- Medications: Most patients use pain medication and a muscle relaxer for four to six weeks. Avoid anti-inflammatory medications such as ibuprofen, naproxen, meloxicam, celecoxib and diclofenac, which can interfere with fusion. Blood thinners are held for 5 to 7 days after surgery until Dr. Grunch’s team tells you to restart them. Take pain medication with food, avoid alcohol while taking it, and use a daily stool softener.
- Bone growth stimulator: If one is prescribed, the manufacturer will contact you after surgery.
- Driving: You may drive once you are no longer taking narcotic pain medication, and you may ride as a passenger before then.
- Follow-up: Your follow-up visit is about four to six weeks after surgery. Any outside stitches or staples are removed at 10 to 14 days.
Learn how a bone growth stimulator can support your fusion:

Video: Spinal Fusion Patients: Are You Using a Bone Growth Stimulator?, from Dr. Grunch on her Ladyspinedoc channel (YouTube)
Call the office at 470-293-9800 if you have a fever over 101°F, redness, warmth or significant drainage from the incision, calf pain or swelling, constipation that medication doesn’t relieve, new trouble controlling your bladder or bowels, or worsening pain down your leg. Call 911 for chest pain or shortness of breath.
Download your patient packet
Print your patient packet or save it to your phone so you have it before and after surgery. It explains your surgery, includes your post-operative instructions and shows how to reach our 24/7 Virtual Assistant:
See all patient packets to find instructions for other surgeries and our Surgery Day Guides.
Frequently Asked Questions
Why go through the front for a back problem?
The front of the spine gives the most direct view of the disc. It allows the whole disc to be removed and a large spacer to be placed without disturbing the back muscles or the nerves, which is especially helpful at L4-L5 and L5-S1.
Will I have a scar on my stomach?
Yes, but it is usually small and low on the abdomen, often below the belt line. Most patients find it heals well.
Why do I start on a liquid diet?
Moving the abdominal contents during surgery can make the bowels slow down for a short time. Starting with liquids and walking early helps them wake up and prevents a buildup of gas called an ileus.
Will I also need screws in my back?
Sometimes. If extra stability is needed, screws and rods are placed through small incisions in the back, either the same day or as a second stage. Dr. Grunch will tell you before surgery what she recommends for you.
Could I have a disc replacement instead?
Possibly. A lumbar disc replacement is also done through the front and preserves motion for some patients with disc-related back pain and healthy facet joints. Dr. Grunch will tell you whether you’re a candidate.
Take the First Step Toward Relief
If back or leg pain from a worn-out or slipping disc is keeping you from living your life, you have options. Whether you need a treatment plan, a second opinion or a clear explanation of your imaging, Dr. Grunch and the Southern Neurosurgery team are here to help.
Call 470-293-9800 to schedule an appointment or contact us online.
Have a question first? Ask our virtual assistant anything, 24/7.
We see patients across metro Atlanta and North Georgia at our offices in Gainesville, Sandy Springs and South Atlanta (Riverdale). Find the office nearest you.
Related pages: Lumbar fusion · LLIF · TLIF · Degenerative disc disease · Spondylolisthesis · Lumbar disc replacement
This page is for educational purposes only and is not medical advice. It does not replace individualized care from a licensed physician. Please talk with your own doctor about your symptoms. If you have bladder or bowel changes, groin numbness or rapidly worsening weakness, call 911 or go to the nearest emergency room.